
What exactly is the anion gap?
The anion gap is a derived value that helps clinicians interpret the balance of electrolytes in the blood. It is commonly derived from the main ions measured on a basic metabolic panel, especially sodium, chloride, and bicarbonate. Because routine lab tests do not measure every charged particle in the blood, the anion gap estimates the amount of unmeasured anions present.
In basic terms, the anion gap helps reveal whether something is missing from the expected acid-base balance. A low or high result does not confirm a condition by itself, but it acts as an useful diagnostic clue in the emergency setting. That is why an anion gap calculator is often used as soon as blood chemistry results are available.
The calculation is typically based on the difference between positively charged sodium and the combination of chloride plus bicarbonate. Since bicarbonate is a key buffer, changes in its level often reflect a metabolic derangement that needs rapid attention. Emergency clinicians use this value to identify an acid-base disorder before the cause is fully known.
Why emergency clinicians rely on an anion gap calculator
ED practice depends on fast recognition of patterns. The anion gap calculator enables clinicians quickly judge whether a patient may have metabolic acidosis, a serious form of acidemia that can occur in critical illness. It is not merely a number; it is a tool for clinical decision-making.
If a patient presents with confusion, tachypnea, hypotension, or suspected toxin exposure, the anion gap can narrow the differential diagnosis. Along with an arterial blood gas and a basic metabolic panel, it helps determine whether the patient has a primary acid-base problem and whether compensation is appropriate. The result can influence triage, the need for repeat labs, and whether advanced critical care support is needed.
The anion gap is especially helpful because it can offer a quicker signal than waiting for a complete workup. If the anion gap is elevated, clinicians may immediately consider lactic acid elevation, ketone production, renal dysfunction, or toxic ingestion. If it is normal, they may shift attention to bicarbonate loss, chloride excess, or a mixed process. That quick sorting makes the tool valuable in the first minutes of evaluation.
Elevated anion gap compared with standard anion gap: what’s the difference?
A increased anion gap implies that additional acids or acid-related compounds are building up in the blood. This often happens when there is greater production of acids or decreased clearance of them. Common causes include lactic acidosis, ketoacidosis, and renal failure.

In lactic acidosis, excess lactate accumulates when tissues do not receive enough oxygen or are unable to utilize oxygen effectively. In ketoacidosis, the body produces ketones when it cannot use glucose normally. In renal failure, acid removal is reduced, which allows acid compounds to accumulate.
A normal anion gap, often called a non-gap metabolic acidosis, usually points to bicarbonate loss with a compensatory rise in chloride. This is often called hyperchloremic acidosis. In this pattern, the blood may still be acidic, but the missing bicarbonate is replaced by chloride rather than by unmeasured acids. That difference matters because it changes the likely etiology and next tests.
Emergency clinicians rely on the distinction between high and normal anion gap to direct the workup quickly. A high gap often signals acid accumulation from severe systemic disease or toxin exposure, while a normal gap may suggest gastrointestinal bicarbonate loss or renal tubular problems. In both cases, the anion gap is not the final answer, but it helps determine the direction of the search.
Typical emergency triggers of an elevated anion gap
A number of urgent conditions can cause an elevated anion gap, and some require immediate treatment. Of the most important are sepsis, shock, toxic alcohols, and salicylate poisoning. Each can create a dangerous metabolic state that demands rapid recognition.
Sepsis can cause lactic acid buildup when infection leads to poor perfusion and impaired oxygen delivery. Shock from any cause can do the same because of tissue hypoperfusion, which raises anaerobic metabolism and lactate production. In these settings, the anion gap may be an early warning sign that the patient is worsening even before the full picture is clear.
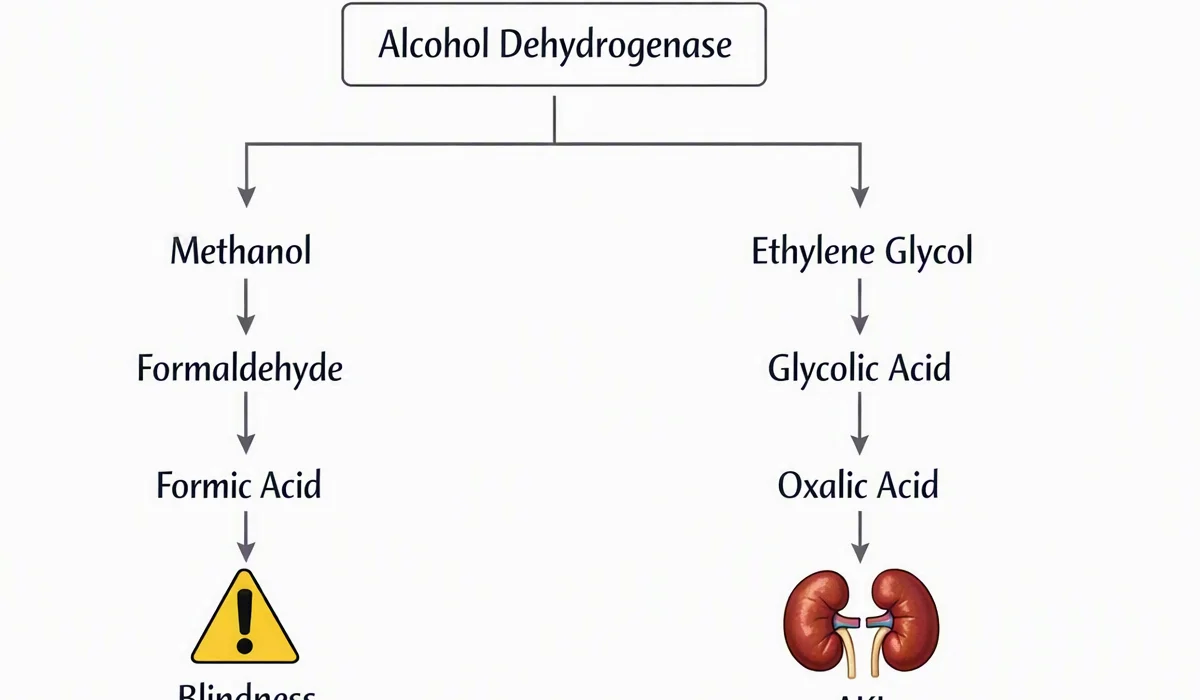
Toxic alcohols such as methanol or ethylene glycol can result in a marked high anion gap through toxic metabolites. These cases are time-sensitive, and early lab interpretation may be the first clue that a poisoning is present. Salicylate poisoning can also produce an elevated gap and a complex acid-base pattern, sometimes including respiratory alkalosis and metabolic acidosis together.
Because these causes are potentially life-threatening, an increased anion gap should trigger immediate attention to the patient’s symptoms, vital signs, and exposure history. The Anion Gap Calculator helps clinicians move from a vague complaint to a focused list of dangerous possibilities.
How to interpret the anion gap in practice
Reading the anion gap requires more than reading a single number. Albumin has a major role because it is a negatively charged protein that contributes significantly to the gap. If albumin is low, the measured anion gap may appear falsely normal or only mildly elevated even when important acids are present.
That is why a corrected anion gap is often more revealing than the raw value. Adjusting for albumin enhances lab interpretation and helps reduce missed diagnoses in patients with critical illness, malnutrition, liver disease, or inflammation. A lower albumin level can hide a clinically important acid load.
Another useful concept is the delta gap, which compares the change in anion gap to the change in bicarbonate. This helps reveal whether another acid-base disorder is also present. For example, a patient may have a high anion gap metabolic acidosis plus a second process such as metabolic alkalosis or normal-gap acidosis.
Clinical context also includes the rest of the lab values. A rising creatinine may support renal failure, a high lactate can support tissue hypoperfusion, and positive ketones can support ketoacidosis. The anion gap is strongest when it is interpreted together with the patient’s symptoms, history, exam findings, and full electrolyte picture.
When a normal anion gap can still be dangerous
A normal anion gap does not mean stability. Significant illness can still be hiding even if the number appears reassuring. For example, diarrhea can cause significant bicarbonate loss and a normal-gap metabolic acidosis that https://anion-gap-calculation.com/causes/low.html causes acidemia. The patient may be critically unwell despite a gap that is not elevated.
Renal tubular acidosis is another key cause of normal anion gap acidosis. In this condition, the kidneys cannot appropriately manage acid or bicarbonate handling. Patients may present with weakness, dehydration, or electrolyte abnormalities that require treatment even though the anion gap does not stand out.
A mixed acid-base disorder can also mask a dangerous process. One disorder may raise the gap while another lowers it, creating a value that looks normal on paper. For example, a patient may have lactic acidosis plus metabolic alkalosis, or a high-gap process plus chloride-driven acidosis. In such cases, the anion gap alone can overlook the full picture.
Chloride is central to recognizing these cases because increased chloride often accompanies bicarbonate loss. If the clinician only sees a normal anion gap, the underlying problem may be overlooked. This is why the electrolyte pattern must always be read as a complete picture, not in isolation.
Why the anion gap is valuable for triage and treatment decisions
In emergency care, the anion gap helps clinicians determine who needs more rapid escalation. A markedly elevated gap may point to a life-threatening process requiring immediate assessment in critical care. Even before the exact cause is known, the result can justify prompt testing, careful monitoring, or ICU-level concern.
The gap also supports early diagnosis. If the clinical picture suggests infection, shock, diabetic crisis, poisoning, or renal failure, the anion gap helps confirm that a metabolic process is underway. This can accelerate treatment choices such as fluid resuscitation, toxin-specific therapy, insulin, dialysis consultation, or repeat assessment of acid-base status.
For monitoring, serial anion gaps can help track whether a treatment is working. If the cause is corrected, the gap may improve as the underlying acid load falls. That trend can be especially helpful in patients with acidemia who are too unstable to wait for slower clinical changes.
Because the anion gap is available from common chemistry testing, it is a useful tool for bedside decisions. It does not replace the exam or more advanced testing, but it gives emergency teams a rapid way to prioritize the sickest patients and to direct the next diagnostic step.
Drawbacks of Anion Gap Calculator interpretation
While valuable, the anion gap is imperfect. A laboratory error can create a confusing result, which is why a repeat test is sometimes required if the number does not fit the clinical picture. Issues in specimen handling, contaminants, or data entry errors can all alter interpretation.

The chosen reference range also matters. Different laboratories may apply slightly different methods and normal values, so clinicians must assess the result according to the reporting lab. A value that looks mildly abnormal in one setting may be normal in another.
The measure is also limited because it captures only some of the chemical balance in the blood. Unmeasured ions may accumulate, but the tool cannot pinpoint them directly. It can hint at their existence, yet it cannot name the exact substance causing the imbalance. That is why the anion gap is a indicator, not a definitive answer.
Ultimately, clinical context always matters. Someone with nausea and vomiting, diabetes, kidney disease, suspected poisoning, or infection may need additional evaluation no matter whether the anion gap is high, normal, or borderline. The most accurate interpretation brings together the calculated value with symptoms, exam findings, and the broader metabolic picture.
Common questions about anion gap in emergency care
What can the anion gap show in emergency care?
The anion gap lets emergency doctors whether there may be a hidden acid-base disorder that is not clear from standard chemistry alone. It is a quick way to look for metabolic acidosis, unmeasured anions, and serious causes such as lactic acidosis, ketoacidosis, renal failure, or toxin exposure. In practice, it aids in sharpen the differential diagnosis and guide urgent next steps.
Why is the anion gap important for diagnosing metabolic acidosis?
The anion gap value is important because it helps separate different types of metabolic acidosis. A elevated anion gap points to added acids are accumulating, while a normal anion gap suggests bicarbonate loss or chloride gain. This distinction improves diagnostic value and helps healthcare providers target the right cause more rapidly.
Can a normal anion gap still signal an important illness?
Indeed. A normal anion gap can still be seen in severe conditions such as loose stools, renal tubular acidosis, or a mixed acid-base disorder. A patient may still have marked acidemia even if the gap is not elevated. That is why emergency medicine teams interpret the anion gap alongside clinical signs, lab values, and the overall clinical picture.
How does albumin affect the anion gap?
Serum albumin can lower or raise the expected anion gap because it is a major unmeasured anion in the blood. When albumin is low, the measured anion gap may appear misleadingly normal. A corrected anion gap accounts for that effect and gives a more reliable estimate of the patient’s acid load.
What causes a high anion gap in the emergency setting?
Typical causes include lactic acidosis from sepsis or shock, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions can create a serious metabolic derangement that requires prompt recognition. The anion gap calculator helps clinicians notice the pattern early and direct the workup.